
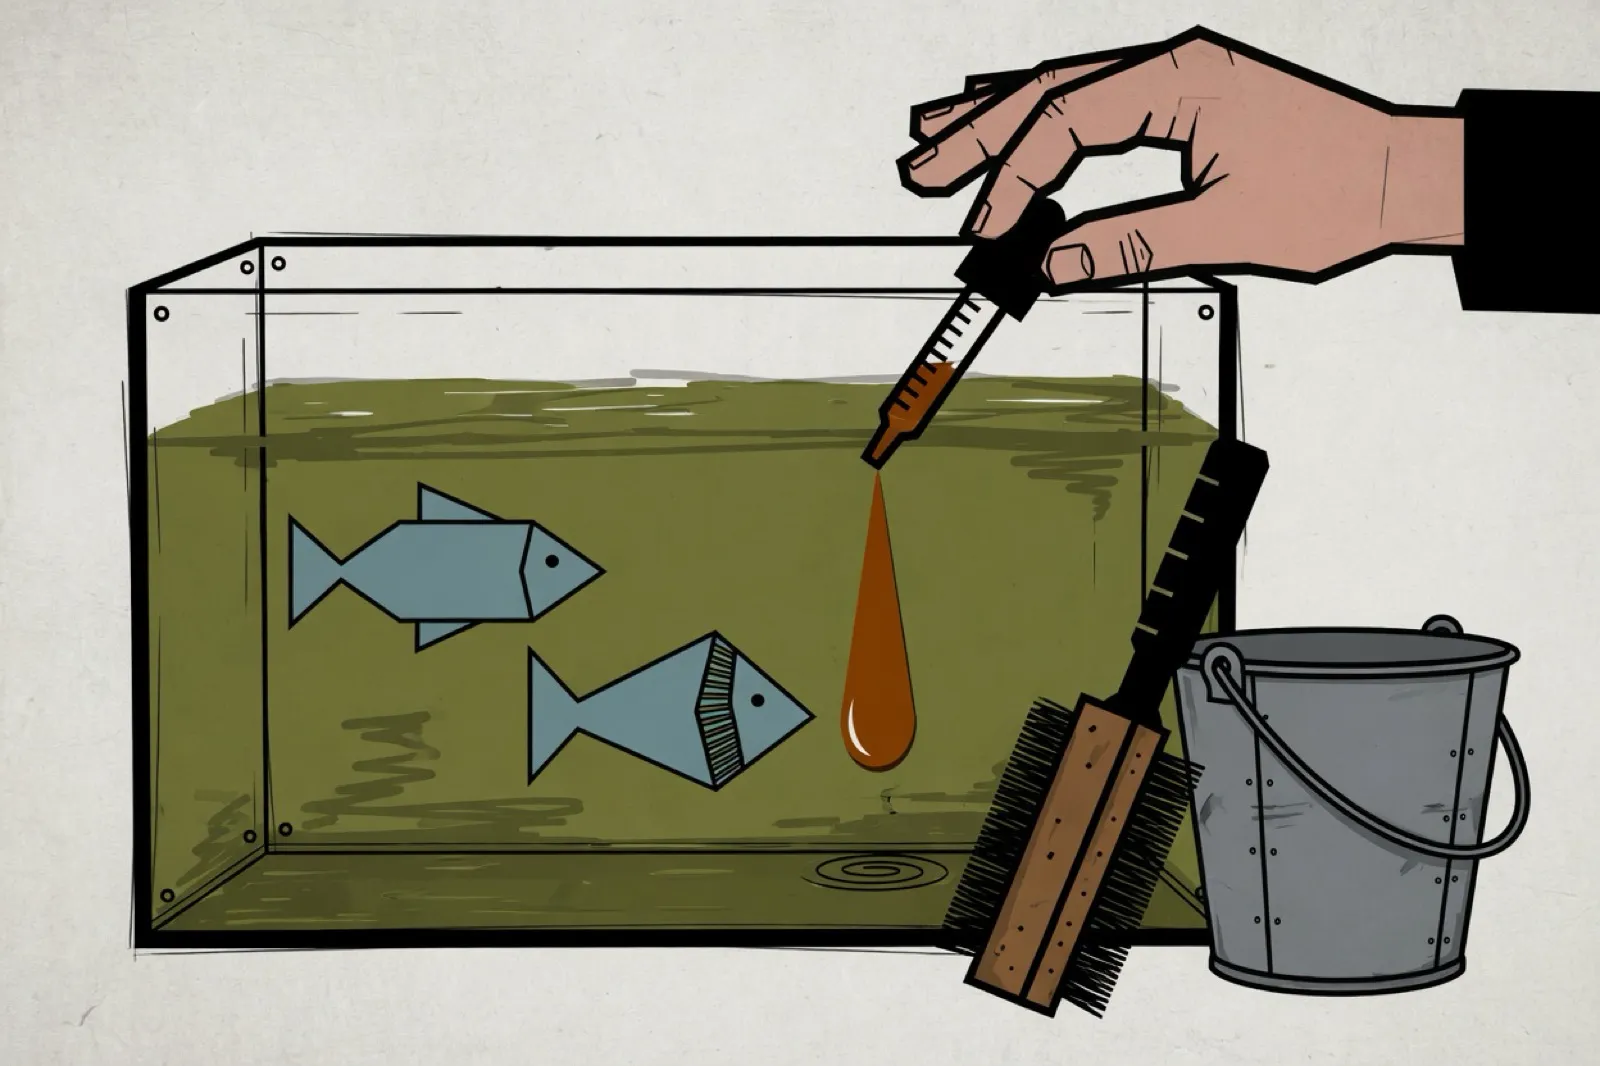
Drugging the Fish Instead of Cleaning the Tank
GLP-1 drugs help many people, but treating a metabolic crisis mainly with weekly injections leaves the dirty tank untouched.
Ozempic and related GLP-1 drugs were developed for type 2 diabetes and are now widely used for weight loss. They help many people. They can lower blood sugar, reduce appetite, and produce real weight loss.
They also leave the environment that made people sick exactly as it was.
The tank is already dirty
CDC figures put adult obesity near 42% in the U.S., with prediabetes at roughly one in three adults. Childhood rates keep climbing. Those numbers describe metabolic dysfunction, which comes out of what we eat, how we move, how we sleep, how much stress we carry, and policies that make ultra-processed food the easy option.
I keep coming back to a dirty fish tank. The fish get sick, so you can dose them with medicine or you can clean the water. In an emergency you might do both. Only the water fixes anything.
The mess here is food environments stacked with calorie-dense, nutrient-poor products, farm subsidies that favor commodity crops and processed ingredients, whole food that is hard to find or afford in a lot of communities, and lives built around sitting. A weekly injection can blunt appetite and improve somebody’s labs. It does not clean the tank.
Side effects, regain, and money
GLP-1s are real medicine. For someone with obesity or type 2 diabetes who has struggled for years, they can change a life. The trouble starts when they become the main answer to a population problem and nobody says out loud what they cost the people taking them.
A large share of users, often cited around 30%, stop within a few months because of nausea, vomiting, or other gut problems. Severe outcomes such as gastroparesis have been reported, and USA Today has tracked lawsuits over long-term digestive issues. Courts and regulators will sort out those claims. What is already clear is that these drugs are not “set and forget.”
European regulators have looked at reports of mood changes and suicidal ideation with GLP-1 drugs. CNBC and others have tied the concern partly to gut-brain pathways, since much of the body’s serotonin is made in the gut. Causality is not settled. Doctors should watch for it and talk about it honestly with the patient in front of them.
Clinical and academic reporting has found that many people regain weight when they stop the medication. The drug did not fail. Appetite and metabolic set points come back once the drug pressure is gone. That leaves lifelong injection as the durable answer, and that is a big thing to accept without an argument.
Bloomberg has reported that the commercial push on obesity indications has been especially intense in the U.S. compared with other regions. That fits a system with high drug prices, weak prevention, and strong incentives to sell disease management.
None of this makes patients who use GLP-1s weak or wrong. Personal care and system design are different problems. My fight is with a system that hands out shots more easily than it fixes food, primary care, and incentives.
Guidelines, ads, and lobbying
Guidelines, advertising, and lobbying all pushed in the same direction.
The American Academy of Pediatrics moved anti-obesity drugs near the front of its advice for adolescents, which The Atlantic covered critically. The argument that followed was about how early and how hard to medicate kids versus doing more about lifestyle and environment. Reuters has separately documented industry payments to obesity specialists and the institutions they work for. That money does not automatically kill the science. It does mean the disclosures have to be public and somebody independent has to check the work, and that goes double when the patients are children.
Drug companies are among the largest spenders on U.S. television advertising. Academic analyses have asked whether that much marketing shapes which questions get asked on air and which get soft-pedaled.
Health policy voices including Calley Means have described industry-backed advocacy that frames wider access to anti-obesity drugs in equity or civil-rights terms, sometimes through partnerships with advocacy groups. Widening access for people who need treatment is a fair goal on its own. What I object to is moral language used to end the argument about prevention before it starts. People should be able to see that happening and say so.
What I’d actually do
GLP-1 drugs help a lot of patients. A society that mostly drugs its way out of metabolic disease is still failing at prevention.
Real food has to become the easy option. That means food policy, schools, workplaces, safe places to move, and produce and whole foods that people can actually get to and afford. It also means looking hard at the farm subsidies that keep ultra-processed supply chains cheap.
Industry money in the rulebook is the other half of the job. Tighten the rules on who funds guideline bodies and continuing medical education, and on the paid speaker networks the industry calls key opinion leaders. More independent research and clearer disclosure will not kill bias, but they thin the fog.
The last part happens between a doctor and a patient. Treat food, movement, sleep, stress, and community as real care, with drugs as one option when they fit. Tell people the side effects, how long the therapy lasts, what it costs, and the chance of regain if they stop. No sales pitch and no lecture.
A system that only treats the fish while the tank stays dirty will always need more drugs. Keep the good medicines available for the people who need them. Stop pretending that is the same as solving the metabolic crisis.